

My illustration entitled: “The Body Under Her Own Hand” – A woman stands before a life-sized clay sculpture of herself, making one deliberate change with a sculptor’s tool. A doctor holds a lamp so she can see the work clearly. A faint double helix is etched into the clay.
If genetic technology becomes capable of changing the human body, who has the strongest presumptive claim to authorize those changes? Consider a competent adult who wants a genetic treatment for a condition she has lived with for years. Her parents fear the consequences. Her physician believes the treatment may help. The company offering it wants her to enrol. Each has a reason to speak. She is the person who will live with the result, and the decision begins with her authority over her own body.
Genomic Sovereigntism begins with the distinction between technological power over DNA and legitimate authority over a person. That distinction also applies when the person wants to change her own biology. Bodily autonomy protects her ability to pursue a change she has reason to value as well as her ability to refuse one. I call the capacity to make informed decisions about interventions to one’s own biological constitution Genomic Self-Authorship. It concerns who decides, what makes the decision genuinely theirs, and what others owe them when they seek to act on it.
The claim to decide
We inherit a body we had no part in choosing. As adults, we make choices about how to care for it, what risks to take with it, and which of its limitations to accept. Genetic intervention would extend some of those choices to an earlier point in the chain of causes. A person might seek to change a process that produces a recurring illness instead of treating each episode as it comes. The biological depth of the intervention gives us reason to examine it carefully. It also makes it especially important to hear from the person whose body would change.
Parents may know the history of a condition. Physicians can explain what an intervention may do. Regulators can demand evidence about safety, and companies have duties to disclose what they know about the products they offer. These roles carry responsibilities of their own. For a competent adult, the authority to give or withhold personal consent ordinarily belongs to the adult. Gratitude for a parent’s care creates no continuing obligation to let that parent decide. A clinician’s recommendation carries the weight of expertise. Its acceptance remains a decision for the patient.
Therapy and enhancement
Research reported this year has shown that targeted changes can be made to DNA in human cells in the laboratory. Separately, researchers have reported early results from gene therapy for metachromatic leukodystrophy, a serious inherited disorder. The clinical study used gene addition. Therapeutic gene editing would seek to alter an existing DNA sequence for a medical purpose. The distinction matters because success in changing cells in a laboratory leaves open whether a particular intervention can safely and reliably benefit a patient. Mali and colleagues, Science, 2013. Biffi and colleagues, Science, 2013.
Suppose a well-supported intervention eventually offers an adult the prospect of preventing a serious decline in health. She may judge a substantial risk worth taking because she knows what that decline would cost her. Another adult with the same condition may put greater weight on keeping the abilities she has or waiting for better evidence. Both decisions can be reasonable. The physician’s task is to help each person understand the alternatives and to judge which options can responsibly be offered. The patient brings knowledge of what those alternatives would mean in the life she actually leads.
Enhancement raises a further question. Imagine an intervention that might increase an adult’s endurance beyond what ordinary training can achieve. Wanting greater endurance can be a considered aim. Its value to the individual still has to be weighed against the uncertainty and possible permanence of the change. A degree of uncertainty that might be acceptable in the face of a severe progressive illness may be difficult to justify for a modest gain in performance. The words therapy and enhancement tell us something about the purpose of an intervention. The ethical judgment also depends on its likely benefit, risks and alternatives.
What informed consent requires
To authorize a genetic intervention, a person must understand what it is intended to change, how much confidence there is in the expected benefit, and what could go wrong. She should understand what waiting would mean, what ordinary treatments remain available, and who would provide care if problems appeared later. Where the evidence comes from a small study or a laboratory experiment, she needs to know what remains uncertain. The 2013 Declaration of Helsinki requires researchers to explain anticipated benefits, risks, conflicts of interest and post-study provisions, and to respect a participant’s right to refuse or withdraw. These obligations matter especially when a person seeking treatment is invited to enter research. World Medical Association, Declaration of Helsinki, 2013.
Irreversibility changes what a person must understand before agreeing. She may be able to withdraw from a study after an intervention has occurred while continuing to live with its biological effects. That distinction should be explained before she commits. She should also have a chance to discuss what long-term monitoring could involve and which complications could be treated. For an elective intervention, time to reflect or seek an independent opinion can improve the quality of the decision. When delay would itself carry a serious cost, that cost belongs in the same discussion.
Consent also depends on how people are treated when they ask questions. A person who wants a second opinion should be able to get one without forfeiting ordinary care. A researcher should disclose a financial interest in enrolment. A company should explain the limits of its evidence with the same clarity it uses to describe an expected benefit. A signature records a decision at a moment in time. The conditions under which it was given determine how much authority it carries.
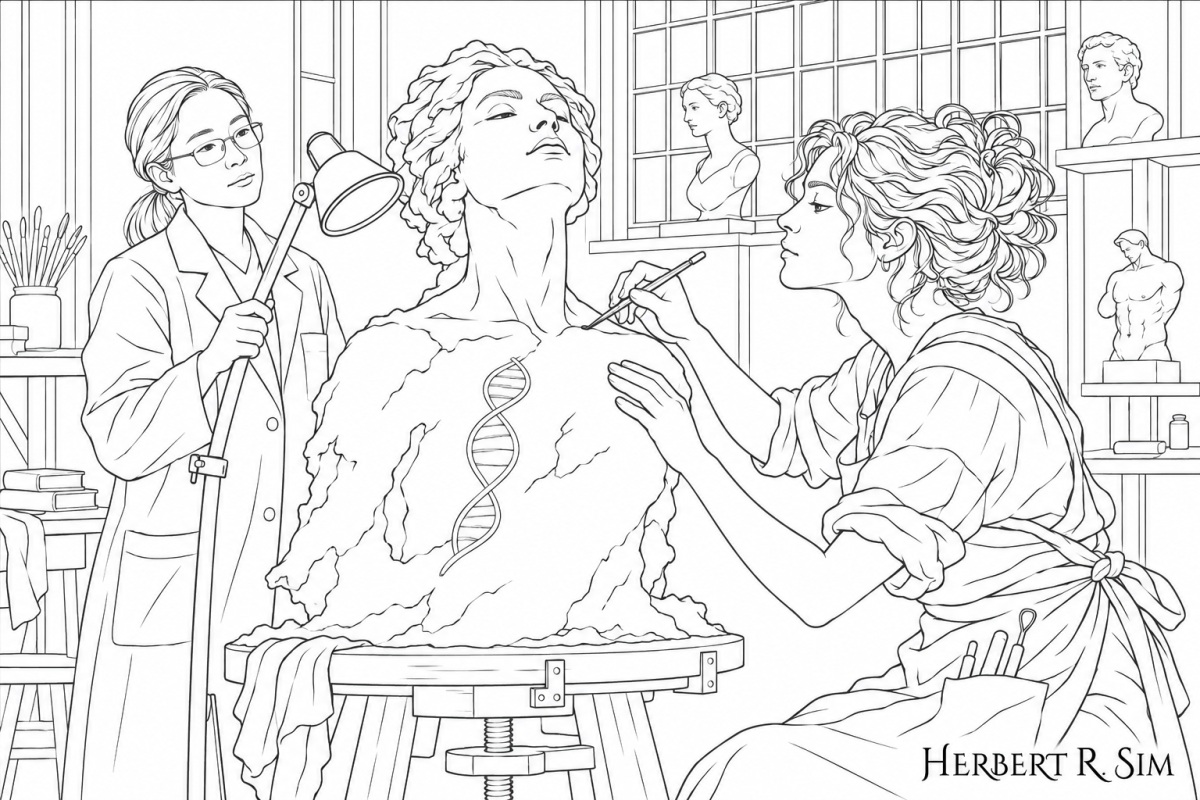
My illustration “The Body Under Her Own Hand” work-in-progress. The art represents that medicine can illuminate the choices, while the authority to reshape one’s own biology belongs to the person who will live with the change.
The freedom to decline
Imagine an employer offering a future genetic enhancement as part of a workplace health programme. The invitation says participation is voluntary. Yet supervisors begin assigning better shifts to employees who accept, and colleagues who decline are asked to explain whether they are committed to the job. A worker who signs up to protect her income may understand the medical facts perfectly. Her ability to refuse has been weakened by the terms of her employment. Asked what she would choose if her livelihood were secure, she might give a different answer.
People already take the wishes of family, colleagues and communities into account when making decisions about their bodies. Someone may freely pursue an enhancement partly because she wants to keep up with friends on a long hike. The issue is whether she has a reasonable way to decline when another party controls something important to her. Loss of a job, education or ordinary care makes refusal costly in a different way from disappointing a friend. An institution that attaches those consequences to refusal needs to justify its own conduct. The burden should never fall entirely on the individual to withstand the pressure.
The right to decline enhancement gives practical force to the right to pursue it. An employer can ask whether a person can perform the work safely. It needs a separate justification for insisting on a particular biological means of doing it. A school can set educational requirements and provide the support that gives pupils a fair chance of meeting them. It should resist making a family’s willingness to modify a child a condition of that support. Where people can continue to take part after declining, an offer of enhancement can remain an offer.
Safety, harm and exploitation
Personal consent is necessary for a voluntary intervention, and a clinician still has to decide whether it can responsibly be provided. A patient who accepts a serious risk deserves a clear explanation if a physician believes the evidence is too weak to proceed. A refusal on safety grounds should identify the specific concern, such as uncertainty about severe adverse effects or the absence of adequate follow-up. Reasons of that kind can be examined and reconsidered as evidence changes. The fact that an adult’s reasons for seeking a change are unusual gives little basis for overriding them.
Some consequences also fall on people who have given no consent. An intervention intended to affect only the consenting adult presents a different question from a change that could be inherited. A proposal that creates a foreseeable and serious risk for others can justify stronger safeguards. The strength of those safeguards should depend on the evidence, the severity of the harm and whether it can be prevented in a less restrictive way. Ordinary demands on shared healthcare resources can be addressed through fair rules about access and funding. The mere possibility that another person may need care supplies a poor basis for giving public institutions general authority over private biological choices.
Exploitation makes another claim on oversight. A person with a worsening illness may reasonably be willing to take a chance, and a provider can profit by overstating what that chance offers. Independent review, truthful advertising and credible plans for follow-up protect the person’s ability to decide on the actual terms. Where an intervention is experimental, the institution should explain who is responsible if something goes wrong. Accepting an honestly described risk never relieves a provider of responsibility for deception, negligence or avoidable harm.
Where self-authorship ends
The argument changes when the person choosing an intervention and the person who will live with it are different. I call that problem other-authorship. A parent who authorizes treatment for a child may be acting out of care and may have to decide quickly to prevent serious harm. The child’s welfare supplies the reason for acting. The parent’s preference for a particular talent or future career supplies a much weaker claim, especially when the intervention could be deferred until the child can decide.
A heritable intervention brings the question into sharper focus. An adult can speak for what she is willing to undergo. Her consent leaves open what is owed to the future people who could inherit the change. That question deserves its own treatment. The distinction begins with identifying whose body is affected, who bears the consequences, and whose purposes the intervention is intended to serve.
Genomic Self-Authorship
Genomic Self-Authorship is the capacity of a person to make informed and voluntary decisions about interventions to their own biological constitution, including the freedom to pursue, decline or defer a change.
A competent person holds the strongest presumptive claim to authorize such an intervention. That claim is exercised within limits justified by clinical safety, the prevention of serious harm to others and the protection of people from exploitation. It has force only where a person can ask for an honest account of the consequences and can say no without surrendering the ordinary terms of social life.