

My illustration entitled: “The Table of Five Hands” – Viewed from above, a patient holds a consent form, a guardian steadies a child’s chair, a clinician points to a risk, a regulator lays down a binding rule, and an inventor holds a tool. Each hand makes a different claim on the same proposed intervention.
Genetic technologies distribute the power to alter human biology among patients, families, clinicians, researchers, regulators, and companies. The people who control the intervention may differ from those who will live with its consequences. Genomic Sovereigntism asks how authority should be allocated in those circumstances, where its limits lie, and when it must pass to someone else. This synthesis brings together eight concepts developed across the series. The Genomic Authority Taxonomy distinguishes the grounds on which different actors can make or constrain decisions. The Genomic Authority Gradient explains why some interventions need a stronger justification than others. Together, they help assess cases in which valid consent, professional approval, legal permission, commercial access, and duties to future persons answer different questions. The theory draws on existing work on autonomy, reproductive liberty, human dignity, non-domination, and intergenerational ethics. Its contribution is to integrate those concerns into a systematic account of legitimate authority over genetic intervention.
1. The problem of authority
Consider an adult offered a genetic treatment. A public regulator permits it, a clinician recommends it, and a company supplies it. The adult refuses. The three approvals give good reasons to regard the treatment as available for consideration. They cannot supply the authorization the adult has withheld. Now consider a child with the same condition who cannot yet decide and may suffer irreversible harm if treatment is delayed. Giving the child’s authority its due in that case may require someone else to act. The question is who may do so, for what purpose, and how much of the decision can be left to the child.
The essay dated 2010 that opens this series began with a distinction between technological capacity and moral authority. The distinction matters in clinical practice. In December 2023, the US Food and Drug Administration approved Casgevy for certain patients with sickle cell disease, marking the first FDA approval of a treatment that uses CRISPR genome-editing technology. A decision of that kind establishes regulatory permission for a specified use. It leaves the patient’s decision, the clinician’s case-specific judgment, and questions of practical access to be settled on their own grounds. [1]
Formal definition
Genomic Sovereigntism is a normative philosophy of genetic technology concerned with the legitimate allocation, limitation and transfer of authority over interventions that alter human genetic constitution.
Technological capacity, biological parenthood, professional expertise, political jurisdiction and proprietary ownership do not, by themselves, confer authority over the person who bears the constitutive consequences of genetic intervention.
Allocation asks who has standing to make a particular decision. Limitation asks what grounds that standing and where it ends. Transfer asks how decision-making should change when, for example, a child acquires capacity, a patient recovers it, or a delegated clinical task ends. An adult can authorize someone to perform a procedure while retaining authority over whether to accept it. When a child becomes able to decide, their standing arises from their own agency. Its exercise need not await a discretionary grant from the people who previously acted for them.
The object of the theory is a decision about an intervention with constitutive biological effects. A person’s genetic constitution helps shape their embodied life. Its relevance can be substantial without exhausting their identity or determining their moral worth. The theory therefore asks who can authorize a change and what it means for the person affected, including when its consequences extend beyond the original recipient.
2. Eight concepts and the questions they answer
| Concept | Meaning | Question it answers |
|---|---|---|
| Genomic Power–Authority Distinction | Practical capacity to bring about a genetic change and legitimate standing to authorize it are distinct. | Does the actor have standing to make the decision their power makes possible? |
| Genomic Self-Authorship | A person with decision-making capacity has a strong presumptive claim to accept, refuse, or defer interventions on themselves. | Can the person make an informed and voluntary choice, including one that declines change? |
| Genomic Other-Authorship | Someone directs or authorizes a genetic change whose constitutive consequences another person will bear. | What entitles the decision-maker to act for anyone beyond themselves? |
| Genomic Authority Gap | Practical power to determine an intervention and exposure to its biological consequences lie with different people. | Can the separation be justified by personal authorization, a limited custodial role, or another defensible ground? |
| Sovereignty–Custodianship Distinction | Authority over oneself and constrained authority exercised for another person arise from different grounds. | What may a substitute decision-maker do, and when should the person affected resume deciding? |
| Genomic Non-Domination Principle | Institutions should prevent avoidable arrangements that give an actor arbitrary or structurally disproportionate control over another person’s biological constitution or future. | Can the person refuse, contest, or leave the arrangement without an avoidable penalty? |
| Genomic Authority Taxonomy | Sovereign, custodial, professional, regulatory, and proprietary claims have distinct grounds, objects, and limits. | Which claim governs the decision in dispute? |
| Genomic Authority Gradient | The justification required depends in part on agency distance, constitutive depth, irreversibility, and heritable reach. | How demanding is the justification, and what must it account for? |
The relationships among these concepts matter. A clinician can have practical control over a procedure that a patient has freely chosen. The Genomic Authority Gap exists in the separation of technician and patient, but the patient can authorize the clinician’s role. The case becomes one of Other-Authorship when the authorization or direction of the change is exercised on the patient’s behalf. Custodianship explains when that can be legitimate. Non-domination asks whether the surrounding arrangements allow the person to exercise whatever authority they have, including after the intervention.
3. The Genomic Authority Taxonomy
A claim to authority should identify its holder, its ground, the decision it concerns, the people affected, and its limits. Hohfeld’s analysis of legal relations is useful here because a claim, a permission, and a power can have different consequences even when ordinary speech calls each a right. The taxonomy extends that analytical distinction into a normative inquiry. A legal right may explain what an institution can lawfully do. Moral authority depends on why the institution may exercise that right in the particular case. [2]
| Claim | Ground | Scope and limit |
|---|---|---|
| Sovereign | The affected person’s standing over their own embodied life. | Authorizes acceptance, refusal, or deferral for oneself. Consent does not compel provision or settle significant risks imposed on others. |
| Custodial | A justified responsibility to act for someone who cannot make the decision. | Permits a bounded decision guided by the person’s wishes where known, welfare, and developing or returning agency. Its scope changes with their capacity and the costs of delay. |
| Professional | Relevant competence and duties attached to clinical or scientific practice. | Supports judgments about evidence, safety, responsible provision, and procedures within the agreed scope. The affected person’s permission must come from its proper source. |
| Regulatory | A publicly justified and accountable mandate. | Establishes boundaries and safeguards for practice. Jurisdiction supplies no proprietary claim over citizens’ bodies. |
| Proprietary | Rights over defined inventions, tools, resources, or services. | May delimit licensing or supply. Control of a resource supplies no authority over the person who depends on it. |
| Prospective claims | Foreseeable interests of people who may bear future effects. | Grounds duties of justification and protection. It does not supply an act of consent by someone unable to exercise agency. |
Non-fungibility. A claimant can satisfy an authorization requirement only by having legitimate standing over the decision to which that requirement applies. Expertise can inform consent. It cannot replace it. A regulator may prohibit a poorly supported practice, and a clinician may reasonably refuse to perform it even where the law permits it. A patent licence may clear an obstacle to using an invention, but its object remains the invention. Parental authority depends on duties to the child and cannot expand into sovereignty over the child’s constitution. For its parties, the Oviedo Convention illustrates the distinction between consent and public limits by addressing them separately. The WHO’s genome-editing recommendations likewise treat equitable access and licensing as governance questions. [3, 4]
These claims need not be ranked in a single hierarchy. A competent adult’s informed refusal is ordinarily decisive for a proposed elective intervention on that adult. A justified professional refusal may independently prevent the clinic from providing it. Both can be decisive within their scope. A favourable result in one domain cannot compensate for a defect in another. Nor does every actor have a veto over every decision. A supplier with a legitimate interest in a contract has no general standing to decide what the patient may do with their own body.
Prospective claims deserve explicit recognition without being treated as a sixth source of operative authorization. A future person’s welfare can give present actors a reason to prevent serious harm, preserve options, or decline an unjustifiable risk. The interest can be represented imperfectly through public deliberation and independent scrutiny. Such representation does not amount to consent by the future person, and its value depends on how openly it confronts uncertainty and disagreement.
4. The Genomic Authority Gradient
The taxonomy identifies whose authority is relevant to what. The gradient assesses how demanding the exercise of that authority should be. An intervention chosen by the person who will bear its effects raises a different authorization problem from one imposed before the person can participate. Its effects may still be serious, difficult to reverse, or capable of reaching others. Each dimension draws attention to a separate reason for scrutiny.
| Dimension | What to assess | What a higher burden asks of the decision-maker |
|---|---|---|
| Agency distance | How far practical control over the decision lies from the affected person’s informed, voluntary judgment. | Explain why another actor has standing, how the person can participate, and why the decision cannot reasonably be left to them. |
| Constitutive depth | How extensively the expected effects shape enduring bodily functions, development, or the conditions under which the person can act. | Identify the functions or capacities at stake, the evidence for the expected effects, and the realistic alternatives. |
| Irreversibility | How realistically the person can later reverse the change, mitigate its effects, or leave a relationship made necessary by it. | Explain what can be undone, what cannot, and what control remains available after the intervention. |
| Heritable reach | Whether and to what extent the change could be transmitted to descendants. | Account for inherited benefits and burdens, uncertainty about future circumstances, and limits on present representation. |
Other things being equal, a rise on any dimension increases the justificatory burden relevant to that dimension. The gradient is a qualitative comparison. It supplies no basis for adding four scores or treating a lower burden on one dimension as payment for a missing authorization on another. An adult’s voluntary choice can reduce agency distance while the intervention remains profound and permanent. A narrowly targeted intervention on a child may be easy to describe biologically and still require substantial justification if the child cannot decide and the benefit can safely be deferred.
Depth and irreversibility must also be distinguished. A lasting change can have a narrow effect. An intervention intended to be reversible can substantially affect development while it is in use. Likewise, a small change in sequence can have substantial consequences, and a relatively contained genetic change can be transmissible. The proposed effect, the affected person’s circumstances, and the quality of the evidence matter more than the number of changes made. An uncertain effect should be recorded as uncertain. Calling it shallow because the evidence is incomplete would turn a lack of knowledge into a reason for confidence.
The comparison must include the harm of doing nothing and the cost of waiting. A durable intervention that can avert otherwise irreversible harm may be easier to justify than a less durable intervention with no comparable benefit. The gradient increases what must be explained. In an urgent case, the explanation may be strong precisely because delay would take away the person’s ability to exercise meaningful agency later.
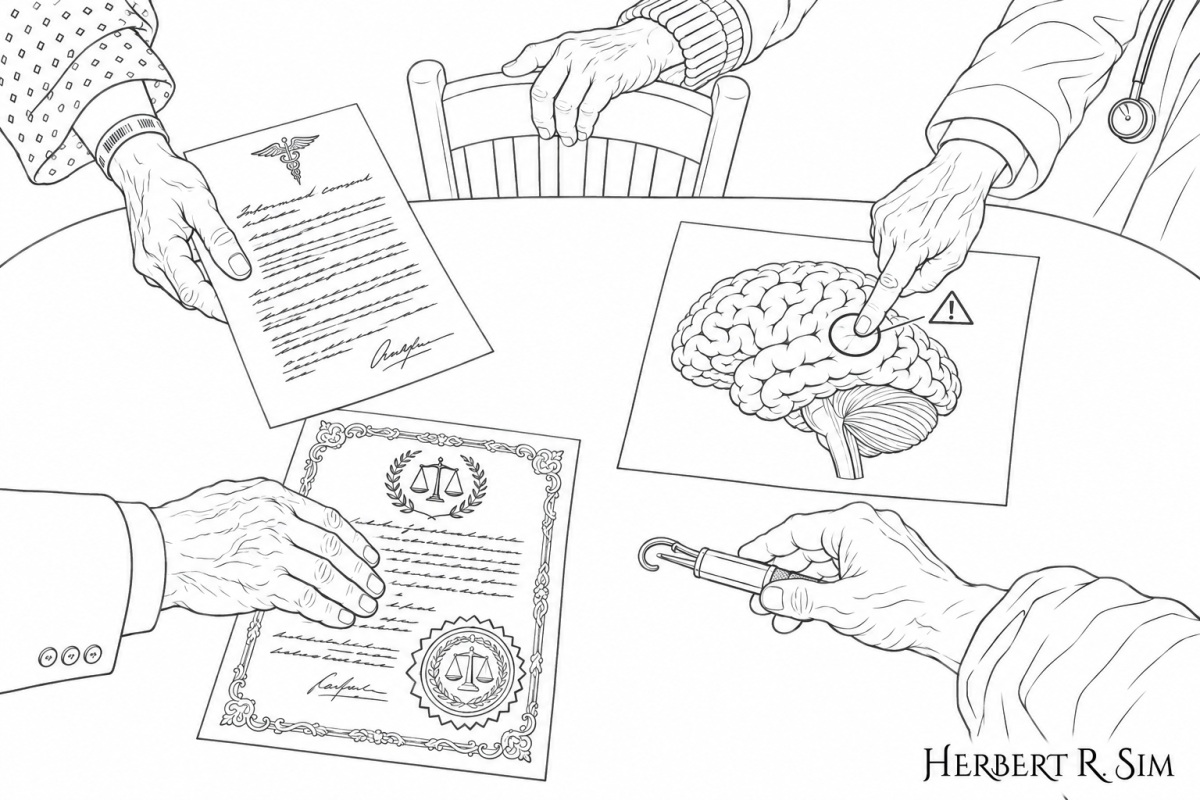
My illustration “The Table of Five Hands” work-in-progress. The art represents that five people can play a role in a genetic intervention, but authority begins with the person who will live with its consequences.
5. How the framework applies
Somatic treatment and continuing authority
Imagine an adult considering a durable somatic intervention for an inherited disorder. The adult understands the proposal and wants to proceed. Agency distance is low, which supports taking their judgment seriously. Constitutive depth and irreversibility may nevertheless be substantial. The clinician must explain the expected effects and alternatives, what follow-up is needed, and what refusing further procedures could and could not change. A regulator’s approval of the treatment cannot answer those questions in the individual case.
Suppose a supplier later conditions necessary follow-up on a separate agreement to use the patient’s genomic data commercially. A new issue arises after the original consent. The company can exert leverage because the person cannot easily escape the consequences of the earlier intervention. Non-domination directs attention to the conditions of refusal. If an independent provider could safely take over, giving the patient access to the information needed to transfer care would restore a meaningful choice. The original treatment authorization does not by itself extend to the new use of data.
Childhood care and competing reasons to act
Consider a child with a progressive inherited condition. An intervention could prevent serious harm, and waiting until the child can decide would substantially reduce the expected benefit. Custodial authority can be justified by the child’s interests and the consequences of delay. The child should have an opportunity to understand and express views to the extent they can. Good reasons to treat the child now can coexist with a duty to leave later choices about additional procedures to the person who will make them. The distinction between parental permission and childhood assent in paediatric ethics supports this account of increasing participation. [5]
Now suppose the proposed change is an enhancement that the parents expect will confer a competitive advantage, and it can be safely deferred. The same family relationship exists, but the reason to exercise custodial authority is much weaker. Waiting preserves both the option and the child’s eventual judgment. The intervention’s purpose matters because it helps establish the stakes of delay. Whether it is described as therapy or enhancement cannot, on its own, settle who should decide.
Reproductive genetics, embryo editing, and germline modification
Genetic counselling, embryo selection, and embryo editing are different acts. Counselling supplies information. Selection can affect which child comes into existence. Editing changes the genetic constitution of the embryo on which it is performed. Where a change can be transmitted, the decision also raises a germline question. Embryo research without reproductive use and a clinical proposal intended to result in a birth therefore require different analyses. Distinguishing them helps prevent authority over one act from being treated as permission for another.
Imagine a future heritable intervention proposed to prevent a severe inherited disease. Even if there were compelling evidence of benefit for the first child, the grounds for authorizing it would have to address the lack of personal consent, realistic alternatives, the implications for the person carrying the pregnancy, and possible effects on descendants. Prospective parents can decide whether to seek reproductive care. The person undergoing a procedure must be able to authorize what is done to their own body. Neither decision answers the claims of future persons by itself. The Third International Summit’s organising committee stated in 2023 that clinical heritable editing remained unacceptable at that time because necessary safety, efficacy, and governance conditions had not been met. The philosophical question would remain even if evidence and oversight improved. [6]
Enhancement, cloning, and engineered human biology
Consider a future enhancement offered to adults whose employer controls access to desirable assignments. Even if opting in is formally voluntary, the employer may create a substantial penalty for refusal. Here agency distance can grow without a formal change in who signs. The relevant evidence includes how assignments are allocated, whether alternatives are available, and whether people who accept the enhancement can leave the job without losing necessary care. Non-domination concerns the employer’s discretion over those conditions, including where it seldom needs to exercise that discretion openly.
Reproductive cloning raises a related authority question even where the act is understood as a way of bringing a person into existence rather than as a modification of an existing patient. Permission to use biological material cannot authorize every reproductive use of it or determine the obligations owed to the resulting child. Genetic resemblance creates no obligation to reproduce another person’s life. The 2021 guidance of the International Society for Stem Cell Research classed human reproductive cloning among research activities that should not be pursued. Its relevance here is to mark the difference between a proposed use of biological material and a reproductive decision whose consequences a person may live with. [7]
Future synthetic or engineered human biology may combine durable bodily changes with an ongoing need for specialised support. In such a case the theory would ask who controls the conditions under which the person can continue to benefit, what happens if the supplier withdraws, and whether the affected person can transfer care. The more deeply the intervention shapes ordinary functioning, the greater the importance of authority after the intervention. Commercial terms can affect that authority even if the original choice was entirely voluntary.
6. What the theory draws from existing bioethics
| Approach | Contribution to the analysis | Question Genomic Sovereigntism foregrounds |
|---|---|---|
| Autonomy | Respect for self-direction supports a strong claim to decide what one undergoes. In principlist bioethics it operates alongside beneficence, nonmaleficence, and justice. [8] | Where does the person’s authority end, and which decisions still require other actors to exercise their own judgment? |
| Informed consent | Consent explains how informed and voluntary authorization can permit an intervention within a defined scope. Research ethics also requires independent scrutiny of risk and participant selection. [9] | Who can authorize which act, and what authority remains with the person when the effects persist after consent is withdrawn? |
| Reproductive liberty | Procreative liberty gives weight to decisions about whether and how to reproduce, including the role of reproductive technology. [10] | What grounds authorize a specific intervention intended to shape the resulting person’s biology? |
| Procreative beneficence | Savulescu argues that prospective parents have moral reason to select among possible children in light of their expected well-being. [11] | When does a reason to pursue an expected benefit also justify a particular actor in deciding, especially where risks extend to others? |
| Right to an open future | Feinberg asks what opportunities and rights adults should preserve for a child to exercise later. [12] | Who will control the options that remain, including access to records, mitigation, further care, and refusal of further participation? |
| Human dignity | UNESCO’s declaration affirms equal dignity regardless of genetic characteristics and rejects reducing individuals to those characteristics. [13] | What authority can be justified while respecting equal standing across different genetic constitutions? |
| Non-domination | Republican theory, including Pettit’s account, treats exposure to arbitrary interference as a threat to freedom even when the power is seldom exercised. [14] | How do lasting biological effects and dependence on institutions change the conditions for meaningful refusal, contest, and exit? |
| Genomic sovereignty | Research on postcolonial genomic policy and Indigenous data governance examines control of samples, information, research resources, and how their benefits are shared. [15, 16] | What gives anyone legitimate authority to perform a genetic intervention on the person who will bear its constitutive effects? |
The distinction from genomic sovereignty warrants emphasis. Ruha Benjamin analyses national genomic sovereignty as a science-policy project, including tensions between national autonomy and reliance on international scientific and commercial networks. Maui Hudson and colleagues address Indigenous peoples’ interests in genomic research, including the governance of access and reuse and the distribution of benefits. These are related lines of inquiry with different claimants and institutional concerns. A national government and an Indigenous community may have different grounds for governing the same research. [15, 16]
Genomic sovereignty, as used in these strands of literature, generally concerns control or governance of genomic information, samples, resources, communities, or populations. Genomic Sovereigntism concerns legitimate authority to perform interventions upon human persons. The two can matter to the same project. A community can have a defensible claim over reuse of a research dataset, while a patient retains authority to refuse an intervention developed using it. The patient’s willingness likewise cannot settle whether the community’s data may be used under disputed terms. Both decisions deserve their own justification.
The originality claim is one of theoretical integration. Genomic Sovereigntism integrates these concerns into a systematic theory of the allocation and limits of legitimate authority over genetic intervention, especially where the decision-maker and the person bearing the constitutive consequences are different persons. Its contribution lies in specifying the decisions to which each form of authority applies, showing why those claims are non-fungible, and explaining how the justificatory burden changes when agency is distant, effects are enduring, or consequences may be inherited.
7. Objections and limitations
Is sovereignty too strong a concept? If sovereignty meant an unlimited entitlement to obtain any intervention, it would obscure duties to others, professional judgment, and public constraints. Here it names the strong presumptive authority of the person over acceptance or refusal of a change to their own body. Its exercise is decision-specific. The term does useful work when it makes clear why agreement among external actors cannot silently displace the person concerned.
Can children possess sovereignty? Children have moral standing from the beginning, and their ability to exercise authority develops unevenly across decisions. A young person may understand an intervention and its consequences in one setting yet need substantial support in another. Custodial authority should narrow as the child’s own agency grows. Age can be relevant in law and practice, while a defensible decision also needs attention to the individual child’s understanding, wishes, and circumstances.
What about emergencies and therapeutic necessity? Urgency can justify acting where a person cannot decide, no timely substitute is available, and waiting would risk grave harm. The justification must be proportionate to the situation and sensitive to any known wishes. The mere description of a proposal as therapeutic supplies no general emergency permission. Emergency reasoning becomes weaker if a less enduring measure could protect the person while preserving an opportunity for later authorization.
Does the theory invite disability discrimination? Judgments about benefit can reproduce social expectations about which bodies are desirable. As Adrienne Asch’s critique of prenatal diagnosis and selection shows, assessments can fail to recognise the lives of people with disabilities or the barriers that society creates. A defensible assessment should distinguish the effects of a condition from the effects of exclusion, hear affected people, and compare clinical proposals with support and accommodation. An argument for preventing a particular harm supplies no warrant for ranking people by their genetic characteristics. [17]
Does it narrow reproductive liberty too far? Adults have serious claims to privacy, bodily integrity, and freedom in reproductive decisions. Demanding justification for a proposed intervention should not make ordinary reproduction answerable to an open-ended public test of parental fitness. The more specific question arises when an actor seeks to authorize a deliberate intervention with foreseeable, enduring effects on a prospective person. Selection also raises questions about who would exist under different choices. The theory can assess what adults are entitled to authorize without assuming that every alternative would have brought the same child into existence.
Can regulation itself become domination? Yes. A public institution can impose excessive restrictions, misuse genomic information, or treat its mandate as authority to direct citizens’ bodies. Regulatory legitimacy therefore depends on reasons open to public challenge, proportionate scope, and meaningful avenues for review. The case for restricting what a clinic can offer and the case for compelling what a person must undergo require different justifications.
What weight should collective consequences carry? Aggregate effects can matter, including unequal access, pressure to enhance, and intergenerational exposure to risk. A defensible response should identify who faces which harms, whether those harms are attributable to a practice, and what measures would address them with the least unnecessary intrusion. A population-level benefit may support funding, monitoring, or restricting a practice. Its size alone cannot establish that a particular person must undergo a genetic change.
Can constitutive depth be assessed consistently? Only imperfectly. It depends on which effect is under review, the timeframe, the available evidence, and the baseline used for comparison. Reviewers should specify the bodily functions, developmental effects, or dependencies they consider material and explain where they disagree. The dimension would become unreliable if used as a measure of how fully human a person is or how valuable their life will be. Its proper object is the reach of an intervention into the conditions of that person’s life.
8. Research agenda and conclusion
The first task is to test whether patients, clinicians, regulators, and independent reviewers can apply the taxonomy consistently to the same cases. Where they disagree, the record should show whether the disagreement concerns the evidence, the meaning of a category, or the principles that govern a contested choice. The gradient can then be tested through paired cases that vary one dimension at a time, followed by harder cases in which several dimensions point in different directions.
A second task is to follow authority through the life of an intervention. That includes studying consent when care depends on a single supplier, transitions from parental decision-making to a young person’s own authority, and what happens to records and continuing care when an institution withdraws. Research should ask patients directly whether nominal rights to refuse, transfer care, or challenge decisions are usable in practice.
A third task is to examine how institutions can account for the interests of future persons without claiming to speak with their authority. Deliberation should include people living with the conditions under discussion, disability advocates, prospective parents, clinicians, and communities affected by genomic research. The work should identify where independent review can improve justification, where uncertainty warrants restraint, and how future people could gain meaningful control over records and decisions that concern them.
Genetic power can relieve suffering and enlarge the choices available to people. Its legitimate exercise requires an answer to a more exacting question than whether a change can be made or whether someone expects a benefit. Those who authorize it must show why the decision falls within their authority, who bears its consequences, and what remains for that person to decide when the clinic, company, family, or state has finished acting.
References
- US Food and Drug Administration. “FDA Approves First Gene Therapies to Treat Patients with Sickle Cell Disease.” 8 December 2023. Announcement
- Hohfeld, Wesley Newcomb. “Some Fundamental Legal Conceptions as Applied in Judicial Reasoning.” Yale Law Journal 23, no. 1 (1913), 16–59. Full text
- Council of Europe. Convention on Human Rights and Biomedicine (Oviedo Convention). 1997, Articles 5, 6, and 13. Treaty text
- World Health Organization. Human Genome Editing: Recommendations. Geneva, 2021, recommendation 6. Report
- American Academy of Pediatrics, Committee on Bioethics. “Informed Consent in Decision-Making in Pediatric Practice.” Pediatrics 138, no. 2 (2016), e20161484. Article record
- Organising Committee of the Third International Summit on Human Genome Editing. “Statement from the Organising Committee of the Third International Summit on Human Genome Editing.” March 2023. Statement
- Lovell-Badge, Robin, et al. “ISSCR Guidelines for Stem Cell Research and Clinical Translation: The 2021 Update.” Stem Cell Reports 16, no. 6 (2021), 1398–1408. DOI
- Beauchamp, Tom L., and James F. Childress. Principles of Biomedical Ethics. 8th ed. Oxford University Press, 2019. Publisher record
- National Commission for the Protection of Human Subjects of Biomedical and Behavioral Research. The Belmont Report. 1979. Full text
- Robertson, John A. Children of Choice: Freedom and the New Reproductive Technologies. Princeton University Press, 1994. Book record
- Savulescu, Julian. “Procreative Beneficence: Why We Should Select the Best Children.” Bioethics 15, nos. 5–6 (2001), 413–426. DOI
- Feinberg, Joel. “The Child’s Right to an Open Future.” In Freedom and Fulfillment: Philosophical Essays, 76–89. Princeton University Press, 1992. Originally published in 1980. DOI
- UNESCO. Universal Declaration on the Human Genome and Human Rights. 1997, Articles 2 and 5. Declaration
- Pettit, Philip. Republicanism: A Theory of Freedom and Government. Oxford University Press, 1997. Publisher record
- Benjamin, Ruha. “A Lab of Their Own: Genomic Sovereignty as Postcolonial Science Policy.” Policy and Society 28, no. 4 (2009), 341–355. DOI
- Hudson, Maui, et al. “Rights, Interests and Expectations: Indigenous Perspectives on Unrestricted Access to Genomic Data.” Nature Reviews Genetics 21 (2020), 377–384. DOI
- Asch, Adrienne. “Prenatal Diagnosis and Selective Abortion: A Challenge to Practice and Policy.” American Journal of Public Health 89, no. 11 (1999), 1649–1657. DOI