

My illustration entitled: “The Shape They Ordered” – A family gathers around a custom mold shaped for a future child. Inside it sits an unfinished clay figure with a faint double helix etched into its back. The figure’s hand reaches beyond the mold’s edge, into open space.
A person can sign a consent form while depending on an employer, insurer, clinic or manufacturer for the ability to refuse. This essay introduces the Genomic Non-Domination Principle, which applies the republican concern with arbitrary power to the authority to direct genetic intervention. It distinguishes domination from persuasion, clinical judgment and legitimate regulation, then examines how public policy, parental decisions, proprietary care and enhancement markets can give others disproportionate control over a person’s biological future. The argument extends the Genomic Sovereigntist distinction between power and authority beyond the moment of authorization. A genetic intervention must be assessed in light of who can set its terms, what happens when the affected person objects, and which dependencies remain after the intervention has occurred.
When permission depends on someone else
Imagine a patient who has undergone a genetic intervention and now depends on a single provider for specialist follow-up. The provider announces that continued care will be available only to patients who agree to participate in further research. The patient is given a consent form and can decline. She also knows that declining may leave her without competent care for an intervention already made to her body. The provider’s ability to control the terms of follow-up changes what her written agreement can tell us about her freedom.
The provider need never issue the demand for the relationship to matter. If it can change the terms at will, the patient may already be reluctant to complain, seek a second opinion or refuse an unrelated request. This is where the distinction between genomic power and genomic authority becomes a question about institutions. Who can set the terms on which a person lives with a biological change? What keeps that power within the scope of the role that originally justified it?
Republican freedom and genomic authority
Republican political philosophy understands freedom in part as security against domination. Philip Pettit’s account asks whether another party has the capacity to interfere arbitrarily in a person’s choices. Someone who depends on a powerful party’s goodwill can be unfree even while that party leaves them alone. Arbitrary power in this sense can be deliberate, predictable and exercised under a written policy. The issue is whether those subject to it have effective protections against having important choices made on terms another party can set unilaterally. [1]
Ordinary influence operates through reasons, example or advice while leaving the other person able to decide. A physician can recommend a genetic test and explain why it matters. The physician can also decline to perform an intervention that the evidence does not support, since professional responsibility governs what a clinician may offer. Legitimate regulation can restrict a procedure on grounds of safety or serious harm to others, with reasons that affected people can scrutinize and challenge. These forms of influence or constraint have purposes and limits against which their exercise can be judged.
Genomic Sovereigntism applies this established political idea to a specific relationship. The person who authorizes a genetic intervention, the institution that supplies it, and the person who will live with its consequences may all be different. An intervention can be irreversible, a decision can precede the affected person’s ability to consent, and specialized care can remain necessary after the original agreement ends. In heritable cases, some effects may reach descendants. The genetics-specific contribution is to ask how authority should be allocated across those decisions and how the affected person can retain or recover control wherever control is possible.
The Genomic Non-Domination Principle
The Genomic Non-Domination Principle holds that genetic technologies and the institutions governing them must prevent avoidable relationships in which one actor acquires arbitrary or structurally disproportionate power over another person’s biological constitution or future. Power is arbitrary when the affected person lacks effective protection against its discretionary use. It is structurally disproportionate when control over an essential service, opportunity or decision gives an actor leverage beyond what its legitimate role requires. Where dependency is unavoidable, institutions must limit that leverage through effective safeguards, independent review and practical means of refusal or redress.
A child’s dependence on parents or a patient’s need for specialist care can be unavoidable. The question is which powers follow from the task of providing that care and which arise from arrangements that could be changed. A clinician may need access to information relevant to treatment. Requiring the patient to surrender unrelated rights as a condition of receiving care exceeds that purpose. The standard asks what power is necessary, what justifies its scope, and what a person can do when it is misused.
States, reproduction and the limits of public purpose
Imagine a government offering reproductive healthcare on condition that people assessed as likely to pass on certain traits agree to sterilization or accept a state-approved reproductive option. The government may invoke lower healthcare costs or the prevention of disease. Its responsibility to protect public health can support making voluntary care available, explaining risks and preventing abusive practices. A person’s dependence on public services gives the government no legitimate basis for using those services to direct that person’s reproductive choices.
Coercion can operate through conditions on care as well as through an explicit order. The 2014 interagency statement on involuntary sterilization, issued by the World Health Organization and other United Nations agencies, identifies people with disabilities and members of other marginalized groups among those subjected to such practices. Its insistence on free and informed decision-making speaks directly to genomic governance. The institutions best placed to identify inherited risks may also control access to the services people need. That combination calls for enforceable limits on how one decision can be made conditional on another. [2]
Parents, children and the authority to provide care
Consider parents who authorize a well-supported genetic treatment for a child facing serious harm if care is delayed. They exercise custodial authority grounded in the child’s welfare. The case for acting depends on the expected benefit, the risks, the alternatives and the cost of waiting. As the child becomes able to participate, their views should carry increasing weight. A decision that preserves the child’s health can also preserve the capacity to make choices later.
A different use of parental power arises when an elective intervention is intended to prepare a child for a specific future the parents want. Suppose they seek an enduring change intended to improve athletic performance, then make family approval dependent on the child pursuing that path. The problem lies partly in authorizing a change that could have waited, and partly in treating the change as a reason the child owes them a particular life. A parent may encourage sport, share an ambition and offer training. The child’s ability to stop matters. Where a biological decision cannot readily be undone, the reasons for making it ahead of the child’s participation must carry correspondingly greater weight.
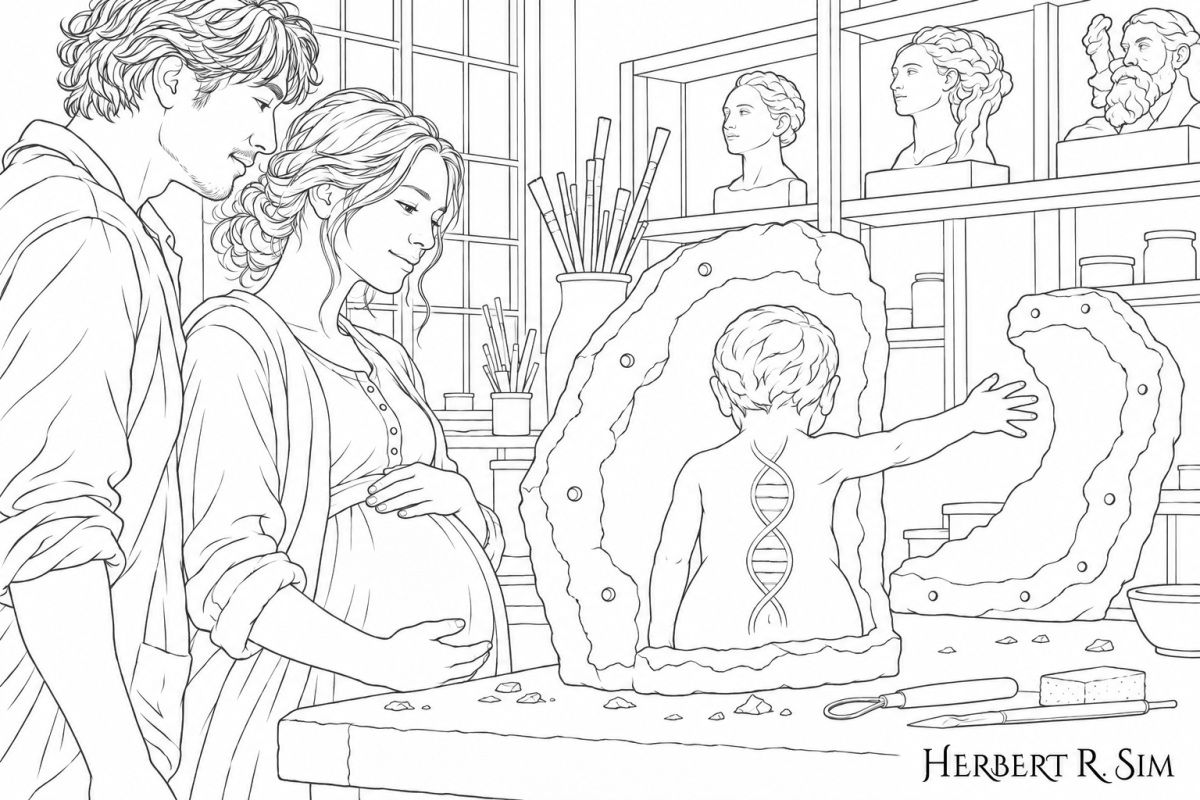
My illustration “The Shape They Ordered” work-in-progress. The art represents that even when parents can shape a child’s genome, the hand reaching beyond the mold signifies the child’s right to shape their own future.
Corporations, clinics and the terms of continued care
Consider a hypothetical therapy whose long-term management requires specialist records and expertise controlled by one company and its affiliated clinic. If a patient moves or wishes to change providers, the company can refuse to make the necessary information available. Its role in developing and supplying the therapy gives it a commercial interest in its work. Exclusive control over the means of obtaining competent follow-up would also give it leverage over decisions beyond that work. It might use the leverage to demand broader access to health data or to prevent a patient from seeking independent advice.
Commercial decisions can alter access even when nobody is trying to compel a patient. In March 2022, the European Commission withdrew the European Union marketing authorisation for the gene therapy Zynteglo at the holder’s request after the company decided to discontinue marketing it for commercial reasons. The withdrawal is an example of how a decision about supply can affect the availability of a treatment. The hypothetical case asks a further question about patients who need continuing care. Who would be able to provide it if the company changes its terms, withdraws or ceases to operate? [3]
That question also applies to medical institutions. A hospital may legitimately recommend follow-up and explain the risks of declining it. It should keep medically necessary care available on defensible clinical terms. When the same institution provides care, recruits for research and decides whether an outside clinician may receive essential records, it is especially important to distinguish those functions. Patients need a way to refuse research, transfer relevant records and challenge a disputed decision without putting their care at risk.
Employers, insurers and compulsory enhancement
Imagine an employer requiring a genetic enhancement as a condition for promotion to work that an employee can already perform safely. The employer has a legitimate interest in performance and safety. It can assess those directly. Requiring a particular biological intervention goes further by making access to income or advancement depend on a bodily decision. The pressure can have the same practical effect if the written policy describes enhancement as voluntary while managers consistently deny advancement to workers who decline.
An insurer can exert a related pressure by using a predictive genetic result to set the terms of coverage. A person may be healthy and able to work while carrying a variant associated with a future condition. If coverage becomes unaffordable on that basis, they may feel compelled to accept an intervention they would otherwise decline. Genetic discrimination can therefore constrain biological choices before anyone orders an intervention. In the United States, the Genetic Information Nondiscrimination Act of 2008 addresses the use of genetic information in covered employment and health insurance. It illustrates how law can limit the ability to turn genetic information into institutional leverage. [4]
The question in both cases is how closely the condition relates to the actor’s legitimate role. An employer may need evidence that a worker can perform a task safely. An insurer may administer coverage under rules that govern how risks are shared. Each should be able to explain why the information or intervention it demands is relevant to that function and why a less intrusive means would be inadequate. Where refusal means losing access to an essential opportunity, scrutiny of that justification matters more than the word voluntary on a form.
Enhancement markets and the cost of saying no
Compulsory enhancement need not begin with a single mandate. Imagine clinics marketing an intervention as a competitive advantage, schools rewarding the capacities it claims to improve, and employers gradually treating those capacities as the expected starting point. Each decision may appear optional when viewed alone. Taken together, they may make ordinary participation increasingly difficult for people who remain unenhanced. The Nuffield Council on Bioethics identified disadvantage, discrimination and social division as relevant to assessing heritable interventions alongside the welfare of the future person. The same questions help explain why a private purchase can contribute to public conditions that constrain other people’s choices. [5]
Competition and social encouragement can influence a decision without dominating it. The concern becomes stronger when institutions tie education, work or care to enhancement despite having reasonable ways to judge ability or provide support. In that setting, responsibility can be shared across several institutions. A school can change an admissions rule, an employer can assess actual performance, and a regulator can examine whether advertising claims are supported. The practical test is whether a person can decline and still exercise the ordinary rights and opportunities for which the enhancement has become an informal condition.
What genomic authority must answer for
Consent answers whether a person authorizes a particular intervention. Governance must also answer who can change the terms surrounding it. Before an intervention, affected people should be able to understand the choices, seek independent advice and decline without losing unrelated services. Afterward, institutions should be able to explain who is responsible for follow-up, how the person can move their care, and where they can challenge a decision. An irreversible change makes those questions more urgent because the institution may retain leverage long after the original agreement.
Where a person cannot authorize the intervention, the justification should be open to scrutiny on their behalf. A parent’s permission needs grounds in the child’s welfare. A public authority’s restriction needs grounds proportionate to the harm it seeks to prevent. In heritable cases, oversight must also consider effects on people who cannot yet participate and preserve the choices they will later be able to make. The World Health Organization’s 2021 recommendations address oversight, international cooperation, registries and intellectual property. Their value for non-domination depends on whether these arrangements constrain powerful actors and give affected people a meaningful way to contest decisions. [6]
How much control a person has over their biological future becomes clearest when they disagree with someone they depend on. Can they refuse an additional procedure, leave a study, change clinicians, or keep a job they can perform? Where the answer depends on permission that another actor can withdraw at will, genomic authority has escaped the limits of the role that was meant to justify it. The responsibility of institutions is to make those freedoms secure enough to exercise when they are inconvenient to the people who hold power.
References
- Pettit, P. (1997). Republicanism: A Theory of Freedom and Government. Oxford University Press.
- OHCHR, UN Women, UNAIDS, UNDP, UNFPA, UNICEF, and WHO. (2014). Eliminating Forced, Coercive and Otherwise Involuntary Sterilization: An Interagency Statement. World Health Organization.
- European Medicines Agency. (2022). Zynteglo: Withdrawal of the Marketing Authorisation in the European Union. EMA/192892/2022.
- United States Congress. (2008). Genetic Information Nondiscrimination Act of 2008. Pub. L. 110–233.
- Nuffield Council on Bioethics. (2018). Genome Editing and Human Reproduction: Social and Ethical Issues.
- World Health Organization. (2021). Human Genome Editing: Recommendations.