

My illustration entitled: “The Moving Line” – a muscular, genetically enhanced man stands barefoot at a clinical height chart that reads 3.30 m. Behind a glass partition, a woman in a charcoal suit stands on a ladder and slides a brass “SUPERHUMAN” marker up its rail.
Imagine two adults offered the same kind of genetic intervention. One hopes to recover muscular strength lost through illness. The other, already healthy, wants greater endurance. The first seeks treatment and the second seeks enhancement. Now imagine that the first adult refuses the procedure, while the second seeks it freely and understands the risks. The medical purpose of the first intervention gives us a reason to offer it. The refusal gives us a reason to stop. In the second case, the adult’s willingness matters even if the proposed use still has to be justified on grounds of safety and professional responsibility.
Much of the debate about genetic technology begins by asking whether an intervention treats a condition or enhances a capacity. That distinction helps explain the purpose of a procedure and the kinds of benefit that might justify its risks. Genomic Sovereigntism asks a further question. Who possesses legitimate authority to authorize the intervention? The person who chooses, the person who bears the consequences, and the person who stands to benefit may be three different people. The distinction between therapy and enhancement cannot tell us how authority should be distributed among them.
What the distinction can tell us
Therapy generally aims to prevent, alleviate, or remedy a condition that threatens health. Enhancement generally aims to extend a capacity beyond some reference level. Both ideas are useful, even though the reference level can be disputed. Consider a hypothetical intervention that reduces susceptibility to infection in a person who is currently healthy. One physician may call it preventive medicine. Another may describe it as enhancement of ordinary immune function. Their disagreement concerns what counts as health or normal function. Neither description settles whether an employer may require the intervention as a condition of work.
The labels matter most when they identify reasons of different weight. A serious illness can make a patient willing to accept uncertainty that would be difficult to justify for a modest advantage. The label “therapy,” however, tells us what an intervention is meant to accomplish. It cannot tell us whether the person understands its risks, whether a refusal is being overridden, or whether some of the consequences will fall on people beyond the intended patient. Those questions remain even when everyone agrees on the clinical purpose.
Adults choosing for themselves
An adult considering gene therapy for an inherited disorder has a strong claim to decide whether to accept the proposed intervention. The physician brings evidence about the condition, the likely benefits, the uncertainties, and the available alternatives. The patient brings knowledge of what the illness means in their own life and which burdens they are prepared to bear. An informed refusal can be reasonable even when the physician believes the treatment offers the better clinical prospect. The 1997 UNESCO declaration on the human genome treats assessing the risks and benefits and obtaining free and informed consent as distinct requirements. [1]
A similar claim applies when an adult seeks an enhancement intended to affect their own body cells. A person may have serious reasons to pursue a capacity they have never possessed. Their willingness has moral weight. It does not oblige a physician to perform a procedure whose uncertainties make it professionally indefensible. The person’s authority over whether to accept an intervention and the physician’s responsibility for whether to offer it can coexist. If either withholds agreement, the procedure lacks a condition it needs to go ahead.
It also matters whether the person can realistically decline. Suppose a company never formally requires a genetic enhancement but makes access to its best-paid work contingent on having it. The worker may still weigh the offer and make a decision, yet the company has changed the consequences of refusal to serve its own purposes. The more serious those consequences become, the less a signed consent form tells us about whose aims are driving the intervention.
Parents treating a child or selecting a trait
Parents sometimes have to decide before a child can give meaningful consent. Imagine a treatment that could prevent progressive organ damage and would lose much of its value if delayed. The case for parents authorizing it rests on the child’s need, the available evidence, and the consequences of waiting. A child able to grasp some of what is proposed should be heard. Where delay is possible and the decision will have lasting effects, there is a reason to leave more of it to the child as their ability to judge develops.
Compare that case with prospective parents who want to select an embryo for a non-medical trait they associate with future success. They might sincerely believe they are improving their future child’s prospects. Julian Savulescu’s argument for procreative beneficence gives serious weight to the expected quality of life of possible children. The difficulty is deciding what adults can reasonably predict and whose values their prediction expresses. A trait prized in a particular profession or social setting may tell us more about the adults’ expectations than about the kind of life the child will have reason to value. [2]
Selection also differs from modifying an embryo. A choice between embryos can affect which child comes to exist. It would be misleading to argue that the child who is born should instead have been born with the genetic constitution of another embryo. There is still a question about the grounds on which the adults made their choice, including whether their reasons depend on treating a particular kind of person as more worthy of being welcomed. The authority question requires attention to the decision that was actually made and what makes its exercise defensible.
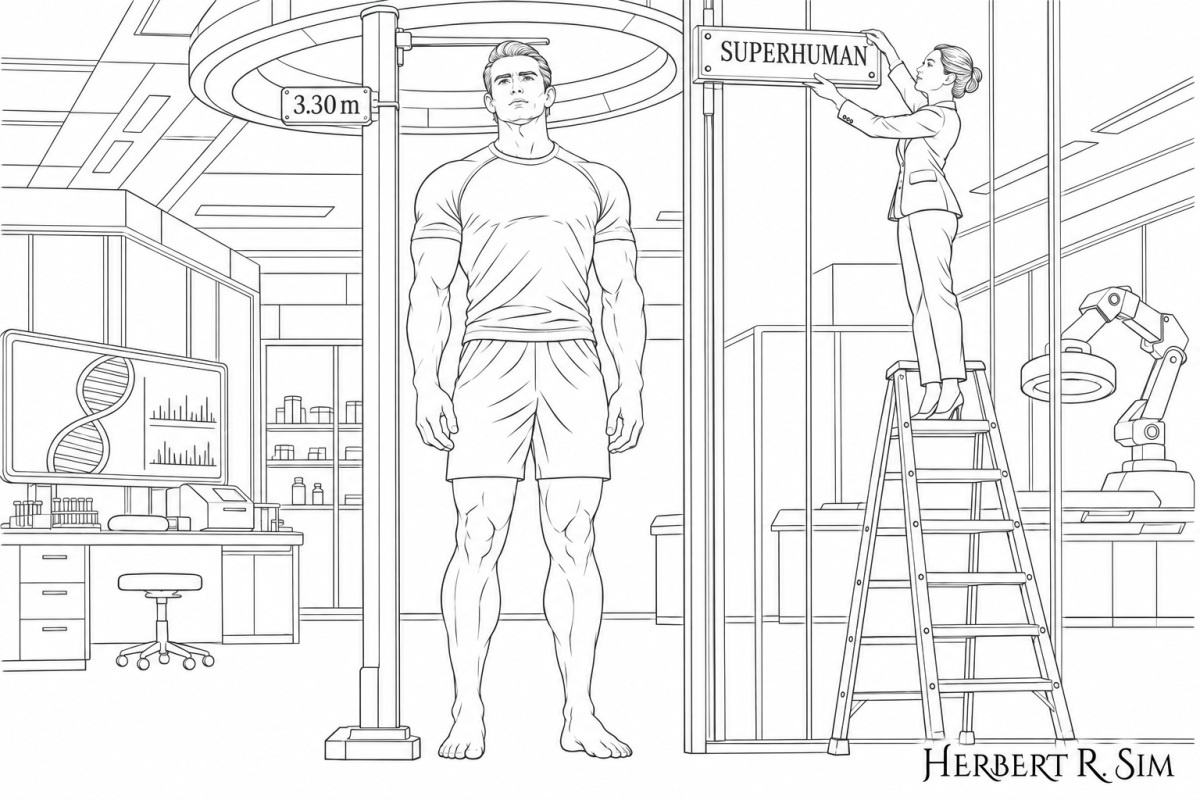
My illustration work-in-progress. The art represents that a person’s height can be measured objectively, while the line between human and “superhuman” is drawn by those in authority.
Embryo modification and germline intervention
Imagine that an embryo could one day be modified to avert a severe inherited illness. Here the reason for intervention might be considerably stronger than a preference for a non-medical trait. The difficulty is that the future person cannot decide, the change could shape development from its earliest stages, and waiting until that person can consent may make the particular intervention impossible. The comparison has to include what can be done later, what risks each option introduces, and the cost of leaving the condition untreated. A serious therapeutic aim supports considering the intervention. It does not answer which adults, acting under which responsibilities, may authorize it.
Where an intervention is capable of affecting the germline, the possibility of transmission adds a further question. A change meant to help the first person could also reach descendants, whose circumstances and interests may differ. An adult’s consent to accept a risk for themselves provides no direct authorization from those descendants. The 1997 Oviedo Convention illustrates how the two issues can be addressed independently. Article 13 limits interventions seeking to modify the human genome to preventive, diagnostic, or therapeutic purposes and excludes those aimed at introducing changes into descendants’ genomes. A medical purpose alone does not meet both conditions. [3]
Reversibility matters on both sides of the therapy and enhancement distinction. An intervention can leave effects that persist after treatment stops. If a person can later discontinue an intervention, reverse some of its effects, or choose among effective alternatives, they retain more room to reconsider. A lasting change made before a person can participate leaves fewer such opportunities. Those who would authorize it owe a fuller account of why it is justified now, especially when a less permanent option could secure a comparable benefit.
How the two questions change the judgment
| Case | Therapy/Enhancement Question | Authority Question |
|---|---|---|
| Adult choosing gene therapy | What disease or impairment would it address? | Does the adult understand the risks and have a meaningful opportunity to refuse? |
| Adult choosing enhancement | What capacity would it extend, and against what baseline? | Is the choice voluntary, and can a clinician responsibly offer the intervention? |
| Parents authorizing treatment for a child | What harm would treatment prevent, and what would delay cost? | What justifies acting on the child’s behalf now, and how can the child participate? |
| Parents selecting a non-medical trait | What advantage is expected, and how reliable is that expectation? | What gives the adults standing to act on this preference, and whose values does it express? |
| Embryo modification | What condition or trait would the proposed change address? | Who can justify an early, potentially irreversible decision for the person who may develop from that embryo? |
| Germline intervention | What benefit is sought, and might the change be transmitted? | Who has standing to authorize consequences that could extend to descendants? |
What a justified decision requires
A reasonable objection is that medicine has long cared for people who cannot consent. If the authority question always blocked action in such cases, it would prevent some of the most important forms of care. Consider again the child facing progressive organ damage. The child’s inability to decide makes the parents’ responsibility to decide intelligible, and there may be good reason for them to act quickly. That authority depends on the need at hand. It does not carry over to an unrelated intervention merely because the same adults would sign the form.
Conversely, willingness is only part of the justification for proceeding. A freely chosen enhancement may still be too uncertain to offer. A proposed treatment may be disproportionate to the condition it addresses. A decision supported by both patient and physician may have consequences for others that call for a further justification. The distinction between therapy and enhancement retains its place because purpose matters to all these judgments. Giving authority its own place prevents a judgement about purpose from doing work it cannot do.
When the person can choose, the question is whether the choice is informed and genuinely theirs. When someone must choose on their behalf, the question is what duties warrant acting now and what is still possible to leave for them to decide. When a change may reach descendants, the inquiry extends to people whose interests cannot be settled by agreement in the clinic. The ethical character of a genetic intervention depends on the benefit it seeks and on whether those who authorize it can justify exercising that authority over the particular lives it will affect.
References
- UNESCO. Universal Declaration on the Human Genome and Human Rights. 1997, Article 5. Declaration
- Savulescu, Julian. “Procreative Beneficence: Why We Should Select the Best Children.” Bioethics 15, nos. 5–6 (2001), 413–426. Article record
- Council of Europe. Convention on Human Rights and Biomedicine (Oviedo Convention). 1997, Article 13. Treaty text